

Understanding Cognitive-Behavioral Therapy (CBT) for Addiction
Cognitive-Behavioral Therapy (CBT) for Addiction is a critical topic in addiction treatment and recovery. According to the Substance Abuse and Mental Health Services Administration (SAMHSA), millions of Americans are affected by substance use disorders each year, and understanding the various dimensions of treatment, including this topic, is essential for informed decision-making about care options.
The landscape of addiction treatment has evolved dramatically over the past two decades. What was once a field dominated by a single approach has become a sophisticated, evidence-based medical discipline that recognizes the biological, psychological, and social dimensions of substance use disorders. This evolution means more options, better outcomes, and greater hope for individuals and families navigating the recovery journey.
This comprehensive guide examines the key aspects of this subject, drawing on current research from the National Institute on Drug Abuse, Centers for Disease Control and Prevention, and American Society of Addiction Medicine. Whether you are exploring options for yourself or supporting a loved one, the information here will help you understand what to expect, what questions to ask, and how to make informed decisions about treatment.

What CBT Is and How It Helps With Addiction
Cognitive behavioral therapy treats substance use as something learned, which means it can be unlearned. It joins two traditions. The behavioral one says use is kept going by what it delivers: relief, reward, escape. The cognitive one says the thoughts that come just before use ("one won't hurt", "I can't cope without it") can be caught and tested. A widely cited clinical review describes the common ground across CBT programs as "learning-based approaches to target maladaptive behavioral patterns, motivational and cognitive barriers to change, and skills deficits" (McHugh, Hearon and Otto, 2010).

In a session this is practical work. You and the therapist map when you use, practice a different response, and you go home with something to try before the next meeting. The same review notes that CBT for substance use relies on "a regular structure, including agenda-setting, identification of goals, and the assignment and review of homework".
The Four Core Elements of CBT for Addiction
CBT is a family of methods, not one script. McHugh and colleagues group what the programs share under four headings.

1. Functional analysis
A map of your use: what sets it off, what you think and feel, what you do, and what follows. The review describes it as "a functional analysis of cues for drug use and the systematic training of alternative responses to these cues". Everything else in treatment is aimed at what this map shows.
2. Cognitive and motivational strategies
Work on the thinking that clears the way for use. The review singles out distortions specific to substance use, including "rationalizing use". Motivational work, such as talking through mixed feelings about quitting, belongs here too.
3. Shifting contingencies
Changing what use and non-use lead to. The clearest example is contingency management, which the review says is "grounded in operant learning theory" and rewards drug-free results with something other than a drug.
4. Skills training
The review sorts skills into three kinds: interpersonal, emotion regulation, and organizational or problem-solving. Refusing an offer is the classic one, rehearsed out loud in the session so it is available outside it.

CBT Skills for Addiction: What You Practice
These are the skills named in the CBT programs the review describes. Most people work on four or five of them, chosen from their own functional analysis.
| Skill | What you do |
|---|---|
| Functional analysis | Write out a recent episode of use link by link, then mark where it could have gone differently. |
| Avoiding triggers | Change routes, routines and contacts so the cue never arrives. |
| Drug and alcohol refusal | Rehearse a short, firm answer to an offer until it is automatic. |
| Cognitive restructuring | Catch a permission-giving thought, write the evidence for and against it, replace it with an accurate one. |
| Problem-solving | Define the problem, list options, pick one, review how it went. |
| Emotion regulation | Name the feeling and ride it out without acting on it. |
| Coping with cravings | Delay, distract, and remind yourself that the urge passes. |
CBT worksheet example: a functional analysis
The worksheet most CBT programs start with has five columns and a line for next time. The entry below is an illustration, not a real patient.
| Column | Example entry |
|---|---|
| Trigger | Friday, 6 p.m., argument with my partner on the phone |
| Thought | "I've had a terrible week. I deserve this." |
| Feeling | Angry, wound up |
| What I did | Stopped at the bar on the way home |
| What followed | Calm for an hour. Then a worse argument, and no sleep. |
| What I will try next time | Call my brother from the car, drive the other route home, and write down what I would say to a friend who told me "I deserve this". |

For skills aimed at the period after treatment, see our guide to relapse prevention, which includes a printable plan.
Does CBT Work for Addiction? What the Trials Show
Yes, with limits that are worth knowing before you choose a program.
The size of the effect
A meta-analysis of 53 controlled trials in adults with alcohol or drug use disorders found that CBT "produced a small but statistically significant treatment effect", strongest among marijuana users and when CBT was compared with no treatment (Magill and Ray, 2009). An earlier review of 34 trials with 2,340 patients put the overall effect in the moderate range.
Compared with what
The most useful analysis is the 2019 update of 30 randomized trials, because it split the results by what CBT was compared against (Magill et al., 2019).
| CBT compared with | Result |
|---|---|
| Minimal or no treatment | Moderate, significant benefit, at both early and late follow-up |
| Usual care or non-specific therapy | Significant benefit in the first six months, not at eight months or later |
| Another specific therapy | No significant difference |

The limits of CBT
Read plainly, the evidence says CBT is much better than nothing, somewhat better than unstructured counseling in the short run, and about as good as the other structured therapies. That is a solid result, not a miracle. It also means the choice between CBT and another well-run evidence-based therapy matters less than whether you attend and whether the program is delivered properly. These trials covered alcohol and illicit drugs. CBT is also used for gambling and other behavioral addictions, but that research is outside what we reviewed here.
Online and computer-based CBT
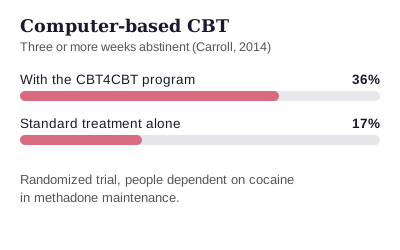
CBT can be delivered by software alongside regular care. In a randomized trial among people dependent on cocaine, those given the CBT4CBT computer program were more likely to reach three or more consecutive weeks of abstinence: 36% against 17% (Carroll et al., American Journal of Psychiatry, 2014).
CBT for Addiction and Trauma
Trauma and substance use often arrive together, and the question people ask is whether to treat one first. A systematic review of 14 randomized trials found that individual trauma-focused cognitive behavioral treatment "delivered alongside SUD intervention" reduced PTSD severity more than usual care, after treatment and at follow-up. For substance use there was no difference straight after treatment but there was one at five to seven months. Two cautions from the authors: fewer people completed the trauma-focused treatment, and the overall quality of the evidence was low (Roberts et al., Clinical Psychology Review, 2015).
In practice that points to doing both together, with a therapist trained in trauma work, and to expecting the trauma sessions to be the harder ones to sit through.

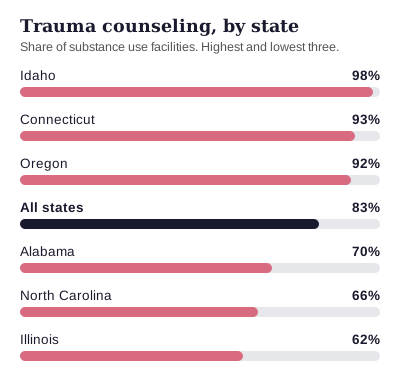
Most programs list some form of trauma care, but the label means different things. SAMHSA asks substance use treatment facilities about trauma-related counseling: 83% of the 7,756 in our directory list it. It asks mental health facilities about programs for people with PTSD and about EMDR: 54% and 26% of the 6,059 list them. If trauma is part of your story, ask before you enroll who delivers the trauma work and with what training.
How Many Treatment Programs Offer CBT
Nearly all of them say they do. SAMHSA asks about cognitive behavioral therapy on both of its questionnaires, the one for substance use treatment facilities and the one for mental health facilities that also treat addiction. Of the 14,140 programs in our directory, 13,174 list CBT. That is 93%, and the share is the same on both questionnaires.
Most other approaches are asked on only one questionnaire, so we give each share out of the programs that were asked. Among substance use treatment facilities, relapse prevention and motivational interviewing are almost as common as CBT. Among mental health facilities, dialectical behavior therapy is listed by 72%.

| Listed in the SAMHSA profile | Programs | Share |
|---|---|---|
| Cognitive behavioral therapy (all 14,140 programs) | 13,174 | 93% |
| CBT and telehealth therapy (all 14,140) | 10,991 | 78% |
| No CBT listed (all 14,140) | 966 | 7% |
| Relapse prevention (7,756 substance use facilities) | 7,406 | 95% |
| Motivational interviewing (7,756) | 7,319 | 94% |
| CBT and trauma-related counseling (7,756) | 6,358 | 82% |
| Contingency management (7,756) | 4,702 | 61% |
| Dialectical behavior therapy (6,059 mental health facilities) | 4,377 | 72% |
CBT by state
The spread is narrow. CBT is listed by 98% of programs in New Jersey and Idaho and by 72 to 73% in Tennessee and Hawaii. Trauma-related counseling among substance use facilities runs from 98% in Idaho and 93% in Connecticut to 66% in North Carolina and 62% in Illinois.
Method: Pathway Recovery editorial team. Source is the service profile each facility files with the SAMHSA Treatment Services Locator (FindTreatment.gov). SAMHSA uses two questionnaires; each share is out of the programs that answered the questionnaire asking about that item: 7,756 substance use treatment facilities, 6,059 mental health facilities that also treat addiction, or all 14,140 when both ask. A program is counted when the approach appears in its profile word for word. Corrected October 16, 2026: an earlier version divided every count by all 14,140 programs, which understated items asked on only one questionnaire by up to half.
Questions to ask about a program's CBT
Because almost every program ticks the CBT box, the label tells you little. These questions tell you more. Is CBT delivered one to one, in a group, or both? Does the therapist follow a manual, and which one? Will I have practice to do between sessions? How many sessions are planned? Is trauma-focused work available if I need it? You can check what a facility reports on its page in our state directory.

The Evidence Base: What Research Tells Us
Modern addiction treatment is grounded in decades of clinical research. Randomized controlled trials, longitudinal outcome studies, and real-world effectiveness data have established clear evidence for what works, and what doesn't, in treating substance use disorders. Understanding this evidence helps individuals and families evaluate treatment options critically and choose programs most likely to produce lasting results.
The NIDA Principles of Drug Addiction Treatment identifies several key evidence-based findings: addiction is a complex but treatable brain disorder; no single treatment is appropriate for everyone; treatment needs to be readily available and retained for an adequate period of time; effective treatment addresses multiple needs beyond substance use; medications are an important element of treatment for many patients; behavioral therapies including CBT are the most commonly used forms of addiction treatment; and treatment must be monitored and modified as necessary.
These principles inform best practices across all treatment settings and substance types. Programs that align with these evidence-based principles consistently produce better outcomes than those relying on unvalidated approaches, ideology, or tradition alone. When evaluating treatment options, ask specifically how the program incorporates these research-backed principles into its clinical programming.
Need Help Finding Treatment?
Our counselors are available 24/7 to help you find the right program.
Practical Considerations and What to Expect
Navigating the practical aspects of treatment can feel overwhelming, but understanding common processes and expectations reduces anxiety and facilitates better decision-making. Whether you are considering residential treatment, outpatient programs, or other care options, several universal practical considerations apply.
Assessment and intake: Quality treatment programs begin with a comprehensive assessment that evaluates substance use history, medical conditions, psychiatric symptoms, social circumstances, and treatment goals. This assessment informs an individualized treatment plan tailored to your specific needs, not a one-size-fits-all curriculum.
Duration of treatment: Research consistently shows that longer treatment engagement produces better outcomes. The National Institute on Drug Abuse recommends a minimum of 90 days for most treatment modalities. However, treatment duration should be based on individual progress rather than arbitrary timelines. Some individuals benefit from 6-12 months or longer of structured care, particularly when co-occurring conditions complicate recovery.
Insurance and cost: Most insurance plans cover addiction treatment under federal parity laws. The treatment center's admissions team can verify your specific benefits and help you understand expected costs. Financial concerns should not prevent you from seeking treatment, numerous options exist for individuals at every income level.
Family involvement: Family participation significantly improves treatment outcomes. Most quality programs offer family therapy, education sessions, and support for loved ones. Engaging family members early in the treatment process builds the supportive home environment that sustains long-term recovery.
Treatment Approaches and Therapeutic Methods
Effective treatment for substance use disorders employs multiple evidence-based therapeutic approaches, typically combined within a comprehensive treatment plan. Understanding the major modalities helps you evaluate programs and participate more actively in your own care.
Cognitive-Behavioral Therapy (CBT) helps individuals identify the thoughts, beliefs, and behavioral patterns that drive substance use. By learning to recognize triggers, challenge distorted thinking, and develop healthier coping strategies, clients build skills that serve them throughout recovery. CBT has one of the strongest evidence bases of any addiction treatment modality.
Motivational Interviewing (MI) is a collaborative conversation style that strengthens a person's own motivation for change. Rather than telling someone what they should do, MI helps individuals articulate their own reasons for wanting recovery and resolve ambivalence about change. This approach is particularly effective in early treatment when motivation may be fragile.
Group therapy provides peer support, accountability, shared learning, and the experience of being understood by others facing similar challenges. Most treatment programs incorporate group therapy as a central element, with groups focused on various topics including relapse prevention, coping skills, trauma processing, and life skills development.
12-step and mutual aid programs including AA, NA, and SMART Recovery provide ongoing peer support that extends well beyond formal treatment. These programs are freely available, widely accessible, and provide a framework for sustained recovery that millions of people have found invaluable.
Holistic and complementary approaches including mindfulness meditation, exercise therapy, nutritional counseling, yoga, art therapy, and equine therapy can complement evidence-based treatments. While these approaches should not replace core therapies, they can enhance overall wellbeing and provide additional tools for managing stress and emotions in recovery.
Building Long-Term Recovery
Completing a treatment program is a crucial milestone, but sustained recovery requires ongoing effort, support, and vigilance. Research published in the Journal of Substance Abuse Treatment demonstrates that the first year following treatment completion is the highest-risk period for relapse, with risk decreasing significantly after five years of sustained sobriety. Building a robust recovery support system during and after treatment is essential.
Aftercare planning should begin well before treatment discharge. A comprehensive aftercare plan includes: ongoing therapy (individual and/or group), medication management if applicable, support group participation, sober living arrangements if needed, employment or educational support, family therapy, recreational and social activities that support sobriety, and a written relapse prevention plan with specific triggers, coping strategies, and emergency contacts.
Lifestyle changes form the foundation of sustainable recovery. Regular physical exercise reduces cravings and improves mood. Proper nutrition supports brain healing. Adequate sleep restores cognitive function and emotional regulation. Mindfulness practices build awareness and stress tolerance. These lifestyle elements are not "nice to have" additions, they are evidence-based recovery tools with documented effectiveness.
Meaningful connection, with a sponsor, therapist, support group, family, and sober friends, provides the social scaffolding that sustains recovery through difficult times. Isolation is one of the most dangerous states in recovery; intentional community engagement is the antidote.
Take the First Step Today
Evidence shows early intervention leads to better outcomes.
Taking Action: Your Next Steps
Knowledge without action changes nothing. If you or someone you love is struggling with a substance use disorder, the most important thing you can do right now is take one concrete step toward help. That step might be making a phone call, attending a support group meeting, scheduling an appointment with an addiction specialist, or simply having an honest conversation with someone you trust.
The path to recovery is different for everyone, and there is no single "right" way to begin. What matters is beginning. Every person now living in long-term recovery once stood where you stand today, uncertain, perhaps afraid, but willing to take that first step.
Call to speak with a counselor who can help you understand your options, answer your questions, and connect you with treatment resources that match your specific needs. The call is free, confidential, and available 24 hours a day, 7 days a week. There is no obligation, and your privacy is protected. Help is available, and recovery is possible.